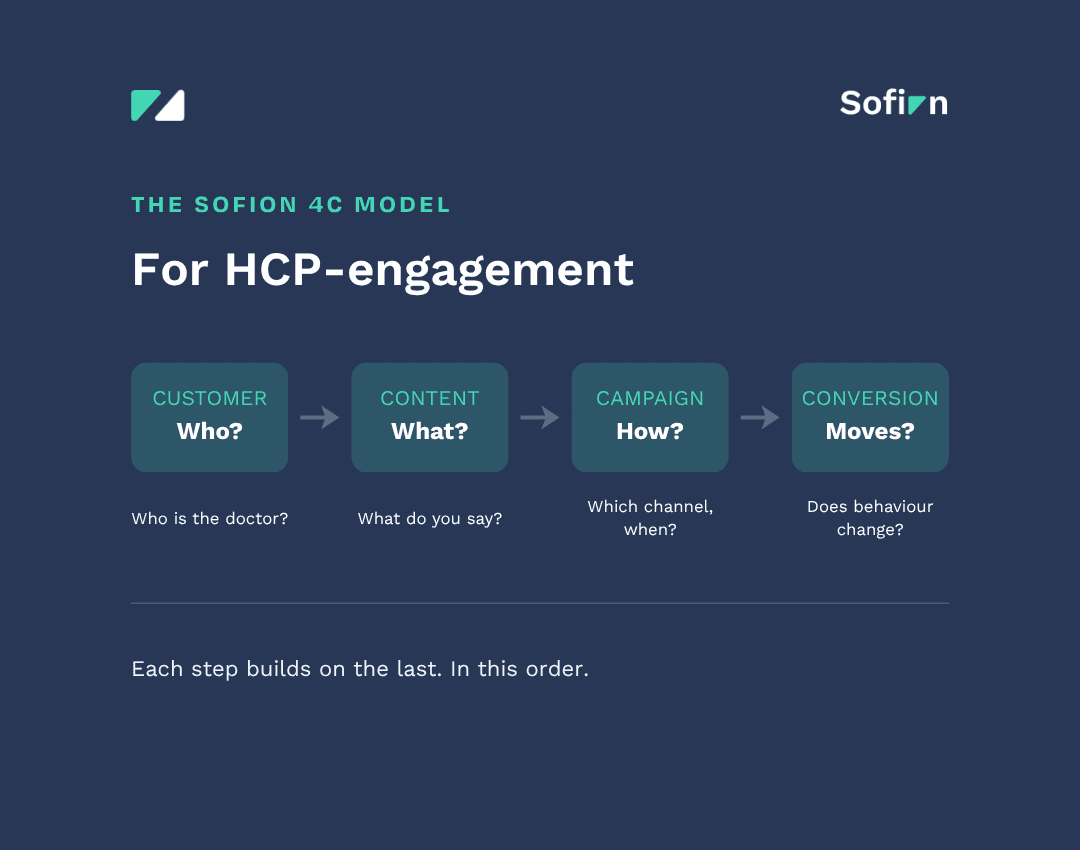
Reaching a doctor is easy. Changing what they do is the hard part. The Sofion 4C model is how we plan education that actually moves a professional, one step at…
Most pharma communication is measured by reach. How many doctors saw it, how many opened the mail. But reach is not behaviour. A doctor can see your message and change nothing. The real question is whether they moved.
That is what the Sofion 4C model is for. It is how we plan education that moves a professional one step further, instead of just adding to the noise. Four steps: Customer, Content, Campaign, Conversion.
Start from the ladder, not the open rate
Behind the model sits a simple idea: a professional moves along an adoption ladder, from Unaware to Aware, Consider, Trial, Adopt and Advocate. The goal is never to “inform”. It is to move someone one rung higher. Everything in the four steps serves that.
Customer: who is the doctor, and where do they stand?
Most teams pick their audience from the top down: all specialists of a certain type. We turn it around and start with the patient. Your audience is not the doctor who already knows the condition, but the doctor who sees the patient without recognising it. Start from real patient numbers and underdiagnosis, find the doctor the patient meets first, and work out which rung of the ladder they stand on today.
Content: what do you say, and when?
The problem is rarely how much content there is. It is the match. The right message at the wrong moment, for a doctor who is not ready, does not land. A doctor who is Unaware needs recognition, not a product. A doctor who is already considering needs the route. Match each message to the rung, and build in a moment to check understanding, so you can see where knowledge breaks and steer from there.
Campaign: which channel, at which moment?
One newsletter changes no practice. Behaviour changes through repetition, in the right order, with deliberate spacing. A campaign is not a single message but a journey of at least three connected touchpoints, spaced a few weeks apart, so the message sticks. And the touchpoints have to come from one architecture, not five separate suppliers, or the thread is lost.
Conversion: does the doctor actually move?
Reach is easy to measure, behaviour is not. Yet behaviour is what counts. So we measure movement on the ladder, not the open rate. We weight each touchpoint by how much it proves real change, combine the numbers with conversations in the field, and steer before the campaign ends, not after.
Why it works
The 4C model is the planning behind the learner journey. It turns “reach is not learning” from a slogan into a method: you know who your doctor is, what they need, how you reach them, and whether they moved. And because it is built on independent, accredited education, it stays within the guardrails of the sector. Where medicines are involved, the communication is CGR-proof.
Put it to work
We made the 4C model into a workbook you can fill in for your own indication, step by step. Request it, and if you want, we sharpen your filled-in worksheets together in a short Discovery session. No sales pitch, just work. Because a missed diagnosis cannot be undone.
Want the workbook? Start a conversation.